I Stopped Drinking Alcohol Every Day (bonus Scary Chart)

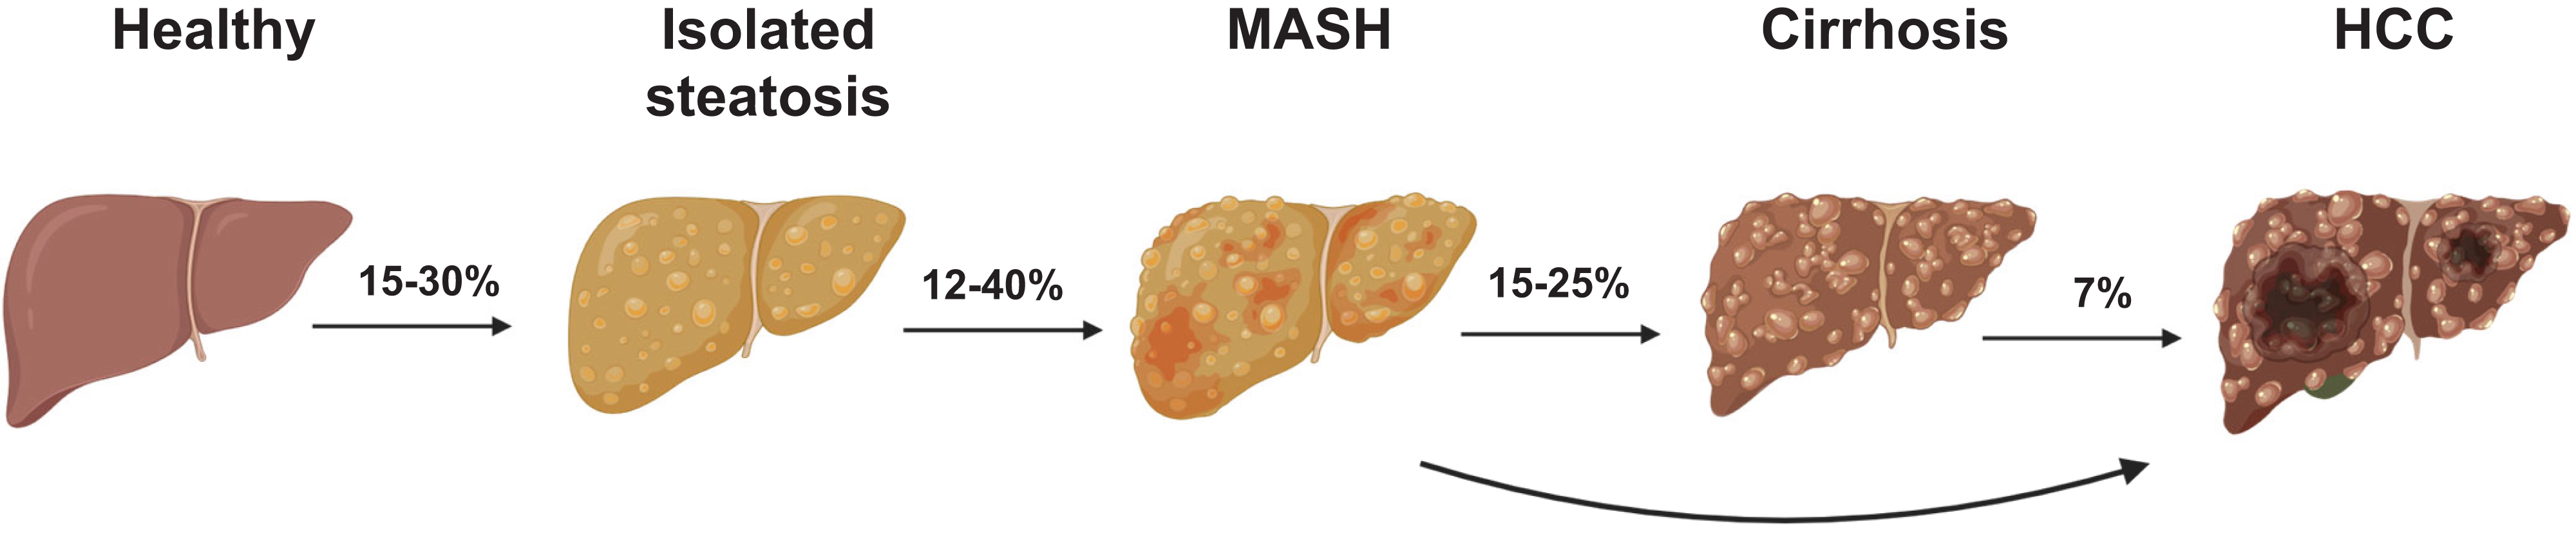
Worldwide, MASLD became the most common chronic liver disease, affecting up to 38% of the adult population (11). In addition, the global prevalence of MASLD is expected to further increase during the next two decades (12). For example, in the U.S., the prevalence of MASLD is predicted to increase from 34% (86 million people) in 2020 to 41% (122 million people) by 2050 (13). MASLD is an increasingly important contributor not only to liver-related but also to extrahepatic morbidity and mortality worldwide. This observation supports that the clinical burden of MASLD clearly extends far beyond the liver, making it a multisystem disorder. While among people with MASLD <10% develop liver-related complications, the major causes of death are CVD and cancer (11,14).

Today, the highest global pooled prevalence of MASLD is found among people with obesity (75% [95% CI 71–79]) (15) and type 2 diabetes (65% [61–68]) (16). Among people with obesity (34% [28–39]) and people with diabetes (32% [17–51]) there is also a very high prevalence of the advanced form of MASLD, metabolic dysfunction–associated steatohepatitis (MASH) (15,16). Furthermore, at 37% (95% CI 26–48), the prevalence of MASLD is also very high among children and adolescents with type 2 diabetes (17). This very early onset of MASLD may have severe long-term consequences for the liver, such as higher risk for cirrhosis and hepatocellular carcinoma (HCC). In addition, among adults with prediabetes prevalence of MASLD is approximately twofold higher in comparison with people with normal glucose regulation, independently of adiposity (18). The findings that overweight and hyperglycemia are tightly related to MASLD indicate that there are joint pathomechanisms promoting adiposity, hyperglycemia, and MASLD. Furthermore, hyperglycemia may promote hepatic steatosis and inflammation, and the steatotic and inflamed liver may also be involved in the pathogenesis of type 2 diabetes. Thus, there may be a vicious cycle between increased liver fat content and insulin resistance–associated hyperglycemia promoting the progression of both diseases.

Norbert Stefan; MASLD as Complication of Diabetes. Diabetes 20 July 2026; 75 (8): 1359–1370. https://doi.org/10.2337/dbi26-0001

The US Health and Human Services (HHS) and Department of Agriculture (USDA) issued new alcohol guidelines in January 2026 “Consume less alcohol for better overall health” and I take advice from my government seriously.
GLP-1 Just $50 a Month!!!

Starting July 1, 2026 Medicare covers certain GLP-1 drugs under the Medicare GLP-1 Bridge program. This temporary program is available nationwide (including all states and U.S. territories) to certain people with Medicare drug coverage (Part D). https://www.medicare.gov/coverage/weight-loss-drugs

You must be 18 or older and meet one of these requirements when you start GLP-1 therapy:


You have a body mass index (BMI) of 35 or more.


You have a BMI between 30-34.99 and have at least one of these conditions:
Diastolic heart failure (also called heart failure with preserved ejection fraction)
Uncontrolled high blood pressure (also called hypertension)
Chronic kidney disease at stage 3a or higher
Prediabetes
A previous heart attack (also called myocardial infarction) or stroke
Blocked arteries in your legs or arms (also called peripheral artery disease) with symptoms


You have a BMI between 27-29.99 and have at least one of these conditions:
Prediabetes
A previous heart attack (also called myocardial infarction) or stroke
Blocked arteries in your legs or arms (also called peripheral artery disease) with symptoms

Yes, I loved writing the click bait title to this post.

Medscape on Obesity – 04.26.26

Medscape on Obesity  
  Latest Stories  
  Study Exposes Risks in Compounded GLP-1s  
  GLP-1s: Are We Losing Too Much Muscle?  
  Can Weight Loss Cut Cancer Risk? New Data  
  A Looming Crisis in Diabetes  
  Non-Medicinal Satiety Tips for Weight Loss  
  Trending  
  New Obesity Medication Guidance: Will It Reduce Stigma?  
  Why GLP-1 Results Vary: New Genetic Data  
  Is Tallow Shallow? The Skinny on Unsaturated Fats  

GLP-1s (it’s kind of a mess)

“But the real question is what is the quality of the weight regain and what is the shift in people’s metabolism, and it seems to be very bad,” she said. “Ongoing studies that haven’t been published yet suggest that hypertension comes back. All the inflammatory markers come back, and lipids go up. And if you have diabetes, it gets worse. Overall, it’s kind of a mess…As these studies and others showed, most people regain the weight. Whether or not they regain all the weight depends in part on diabetes and insulin and many other factors, but people will likely regain most of their weight.”

“But the message isn’t that you regain the weight. The message is that you may be less healthy when you regain the weight. That’s why we need to couple the drugs with lifestyle interventions. And it’s why people who just want to lose 5 or 10 pounds really need to consider that lifestyle change, hard as it is, is the better way to do it.”

Anne Peters, MD, professor Keck School of Medicine of the University of Southern California

Less Weight Regain, More Health Loss after Stopping GLP-1s? – Medscape – March 05, 2026 – https://www.medscape.com/viewarticle/less-weight-regain-more-health-loss-after-stopping-glp-1s-2026a10006rv?

I never envisioned developing an obsession with pharmaceuticals. And after many years of endless blogging into the void I learned I could link to previous posts like this: https://lifeunderwriter.net/tag/glp-1-receptor-agonist/

The learning never stops.

Medscape on Obesity – 02.08.26

  Prescribing GLP-1s After 65? Read This First  
  Beyond BMI: New Tool Flags Hidden Metabolic Risk  
  Is Fat Loss Overrated for Metabolic Health?  
  Digital Tool + Meds Delivered 10%+ Weight Loss  
  Sleep Patterns Tied to Post-Bariatric Surgery Outcomes  
  Discussing Pathways for Patients With Obesity and Depression  
  Trending  
  Do GLP-1s Damage Muscle?  
  What Your Glutes Say About Diabetes Risk  
  Scary Risk That Can Sneak Up on GLP-1 Users  

GLP-1s and the Risk for Malnutrition

“We see cases where people take a GLP-1 medication and become so severely malnourished that they need to be hospitalized,” said Rebecca Boswell, PhD, director of Penn Medicine Princeton Center for Eating Disorders, in Philadelphia. “It’s not uncommon.” The Scary Health Risk That Can Sneak Up on GLP-1 Users – Medscape – January 19, 2026. https://www.medscape.com/viewarticle/scary-health-risk-can-sneak-glp-1-users-2026a10001pi

Yikes.

People return to their baseline weight and lose all cardiometabolic benefits in less than 2 years after stopping semaglutide or tirzepatide, a new meta-analysis found. Weight Regain, Health Benefit Loss Rapid When GLP-1s Stopped – Medscape – January 08, 2026. https://www.medscape.com/viewarticle/weight-regain-health-benefit-loss-rapid-when-glp-1s-stopped-2026a10000kr?

YIKES.

You see, cures are passée. Cures kill markets. Getting the population properly hooked on a pharmaceutical treatment for a ‘chronic’ condition is where the serious money is. “Our core insight was simple and grim: it’s far easier—and infinitely more profitable—to convince healthy people that they’re sick than to develop genuine cures for the truly ill.“

Twenty years later, the hustle is bigger, slicker, and more dangerous than ever. Watching that hustle unfold with weight loss drugs feels weirdly ominous, like watching a slow-moving train wreck you can’t peel your eyes off of. You know there’ll be carnage and bodies, vast fortunes won and lost, and humanity left just a little bit poorer. We have often documented the pharmaceutical industry’s proven ability to create enormously lucrative markets overnight, by inventing and selling diseases. Now watch as all that ingenuity and energy gets pointed at one of the biggest problems bewitching humanity: human fatness. The Seven Deadly Sins of Weight Loss Drugs – https://brownstone.org/articles/the-seven-deadly-sins-of-weight-loss-drugs/

YIKES!

This will not end well.

Complications? What Complications? (just another GLP-1 receptor agonist post)

PATHWEIGH Weight Management Model

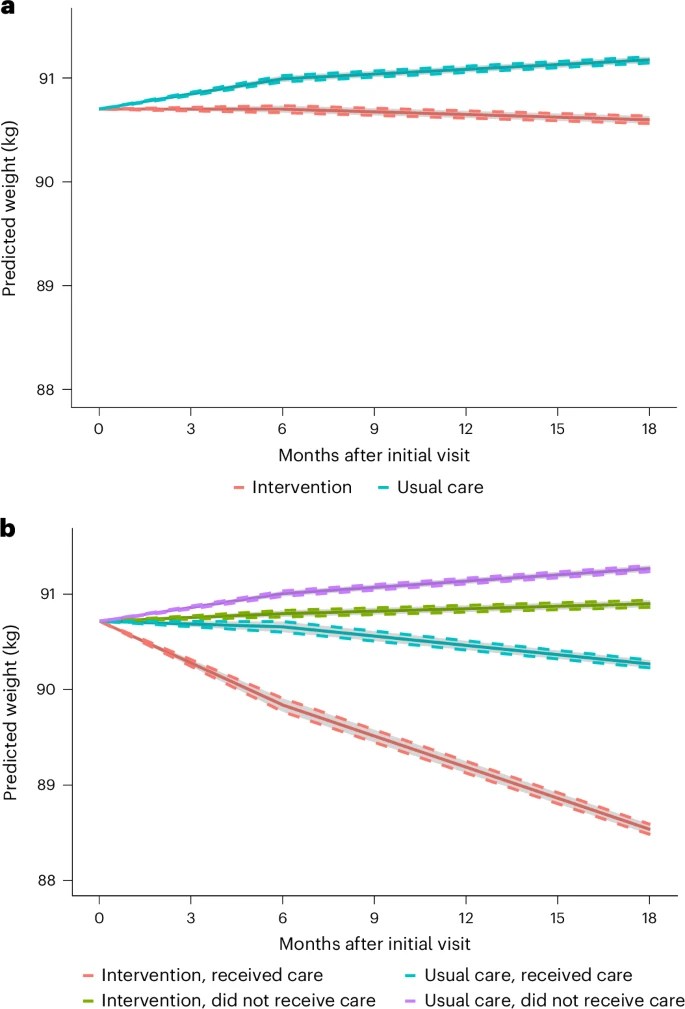
The power of PATHWEIGH is that it puts patients and their primary care provider on the same page…It all started with signage placed in clinics that notified patients that if they wanted to make an appointment to specifically talk about weight management, all they had to do was approach the desk and ask for it. That request automatically triggered a mechanism in the patient’s electronic health record that sent them a survey that after completion would flow into the provider’s notes. Instead of spending so much time typing and talking about the patient’s history, the scheduled visit could be centered around solutions. PATHWEIGH: A Model Changing Weight Management For All – https://news.cuanschutz.edu/medicine/pathweigh-pilot-research

Implementation and effectiveness of a care process to prioritize weight management in primary care: a stepped-wedge cluster-randomized trial – https://www.nature.com/articles/s41591-025-04051-5#Sec1

Medscape 2025 Obesity Articles

  Medscape on Obesity  
  Top Stories 2025  
  Aging & GLP-1s: What Patients Need to Know  
  Anti-Obesity Medications Set to Explode Entering 2026  
  What Comes Back When Stopping GLP-1s?  
  New Obesity Definition Raises the Number Who Have It  
  When GLP-1s Change Patients’ Libido: What to Know  
  Can Creatine Play a Positive Role in Obesity Treatment?  
  New Drug Eases Side Effects of Weight-Loss Meds  
  Does Time-Restricted Eating Cut Extra Belly Fat?  
  High-Fiber Diets and Supplements for Obesity Treatment  
  Most GLP-1 Prescriptions Miss the Mark: Are Yours?