I Stopped Drinking Alcohol Every Day (bonus Scary Chart)

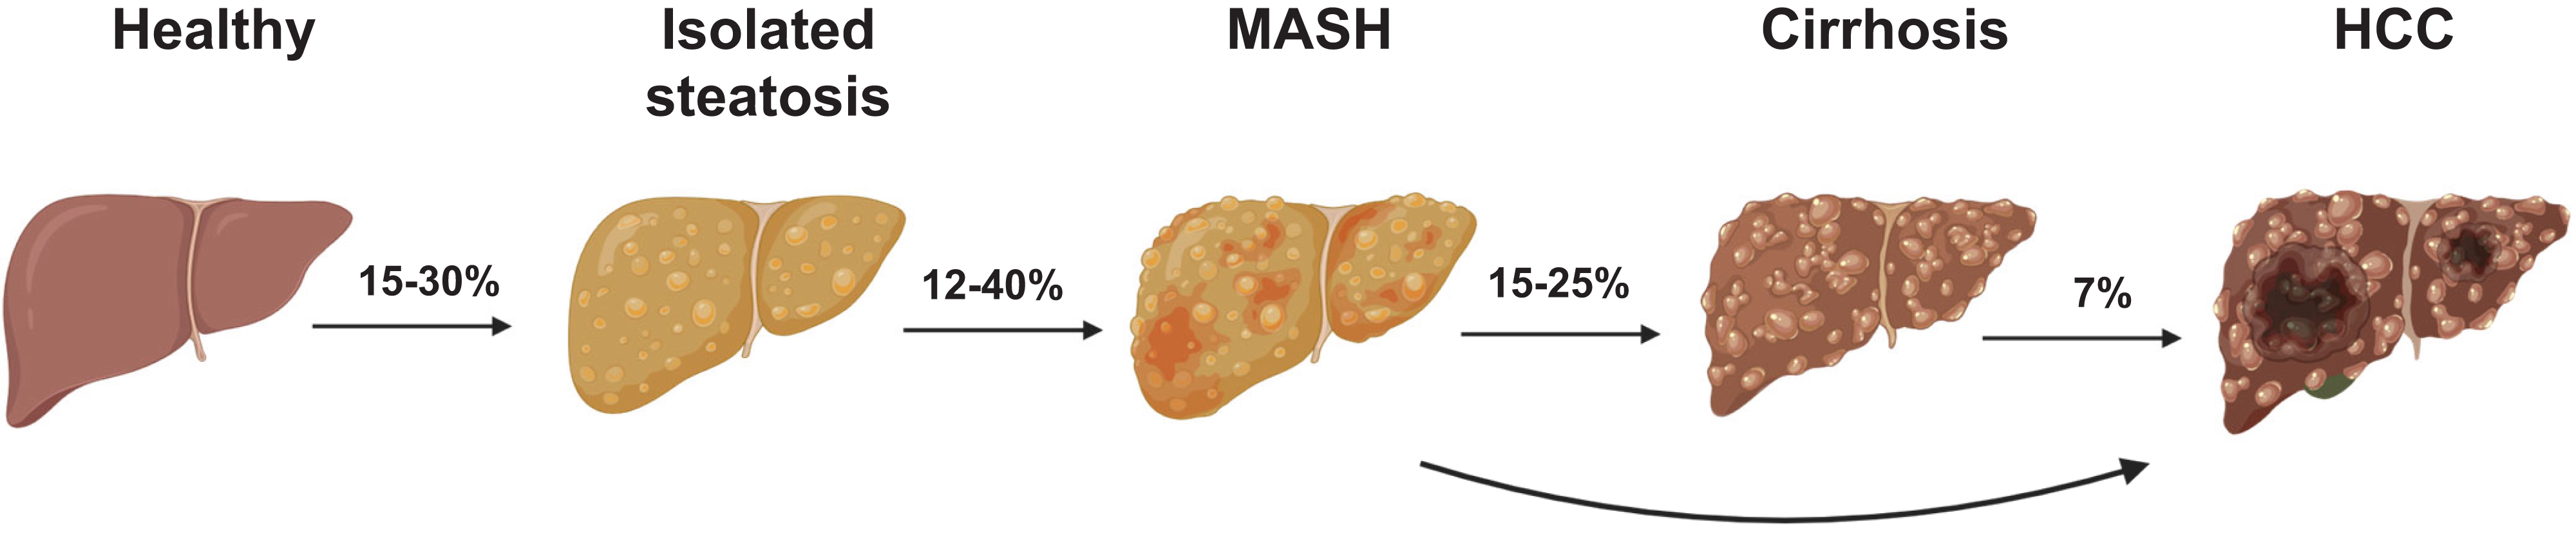
Worldwide, MASLD became the most common chronic liver disease, affecting up to 38% of the adult population (11). In addition, the global prevalence of MASLD is expected to further increase during the next two decades (12). For example, in the U.S., the prevalence of MASLD is predicted to increase from 34% (86 million people) in 2020 to 41% (122 million people) by 2050 (13). MASLD is an increasingly important contributor not only to liver-related but also to extrahepatic morbidity and mortality worldwide. This observation supports that the clinical burden of MASLD clearly extends far beyond the liver, making it a multisystem disorder. While among people with MASLD <10% develop liver-related complications, the major causes of death are CVD and cancer (11,14).

Today, the highest global pooled prevalence of MASLD is found among people with obesity (75% [95% CI 71–79]) (15) and type 2 diabetes (65% [61–68]) (16). Among people with obesity (34% [28–39]) and people with diabetes (32% [17–51]) there is also a very high prevalence of the advanced form of MASLD, metabolic dysfunction–associated steatohepatitis (MASH) (15,16). Furthermore, at 37% (95% CI 26–48), the prevalence of MASLD is also very high among children and adolescents with type 2 diabetes (17). This very early onset of MASLD may have severe long-term consequences for the liver, such as higher risk for cirrhosis and hepatocellular carcinoma (HCC). In addition, among adults with prediabetes prevalence of MASLD is approximately twofold higher in comparison with people with normal glucose regulation, independently of adiposity (18). The findings that overweight and hyperglycemia are tightly related to MASLD indicate that there are joint pathomechanisms promoting adiposity, hyperglycemia, and MASLD. Furthermore, hyperglycemia may promote hepatic steatosis and inflammation, and the steatotic and inflamed liver may also be involved in the pathogenesis of type 2 diabetes. Thus, there may be a vicious cycle between increased liver fat content and insulin resistance–associated hyperglycemia promoting the progression of both diseases.

Norbert Stefan; MASLD as Complication of Diabetes. Diabetes 20 July 2026; 75 (8): 1359–1370. https://doi.org/10.2337/dbi26-0001

The US Health and Human Services (HHS) and Department of Agriculture (USDA) issued new alcohol guidelines in January 2026 “Consume less alcohol for better overall health” and I take advice from my government seriously.

Resistance is NOT Futile (in DM risk)

In this prospective cohort study, resistance training among US adult health care professionals was associated with substantially lower T2D risk, particularly when performed consistently over midlife and combined with adequate aerobic activity and limited sedentary television viewing. These findings support the inclusion of resistance training as a key component of lifestyle recommendations for diabetes prevention. Long-Term Resistance Training and Risk of Type 2 Diabetes – https://jamanetwork.com/journals/jamanetworkopen/fullarticle/2850563

How To Reduce Your DM2 Risk 31%

The results, published in Annals of Internal Medicine, were based on 4,746 adults between ages 55 and 75. All had overweight or obesity and metabolic syndrome, but none had diabetes or cardiovascular disease at the start of the study. Researchers followed participants for six years to see whether a more intensive Mediterranean based lifestyle plan could offer stronger protection against type 2 diabetes than the traditional Mediterranean diet alone.

One group followed a calorie reduced Mediterranean diet (about 600 kcal fewer per day), added moderate physical activity (brisk walking, strength and balance training), and received professional guidance. The comparison group followed a traditional Mediterranean diet without calorie restriction or exercise advice.

The difference between the two approaches was striking. Participants in the intervention group were 31% less likely to develop type 2 diabetes than those in the comparison group. Universidad de Navarra. “Scientists found a smarter Mediterranean diet that slashes diabetes risk by 31%.” ScienceDaily. https://www.sciencedaily.com/releases/2026/05/260519003103.htm (accessed May 23, 2026).

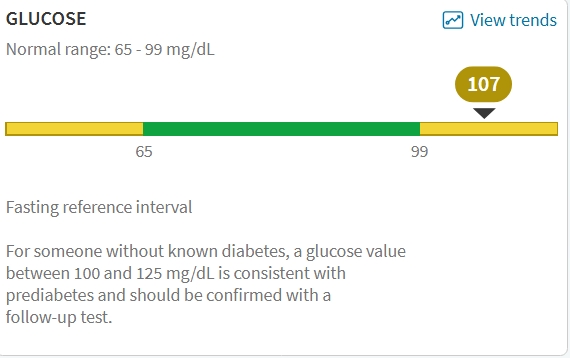
I just had my annual wellness check and got my lab results. All good except my fasting glucose.

Yikes. Memo to Self, get an A1C. Well, the very next day…

Doc says:

CMP (Comprehensive Metabolic Panel): Your creatinine (a measure related to kidney function) is low, and your blood sugar (glucose) is high; all other values are normal. This test checks how your kidneys and liver are working, your body salts, proteins, and blood sugar. Low creatinine can happen in people with less muscle and may be expected. The slightly high fasting blood sugar could indicate early changes in how your body handles sugar. Options include repeating the blood sugar test next visit.

I know my diet could be better. I know I should eat less, snack less and maybe, just maybe stop drinking beer. But also knowing my IFG is worsening I wondered if there was a diet (besides MedDiet) for IFG?

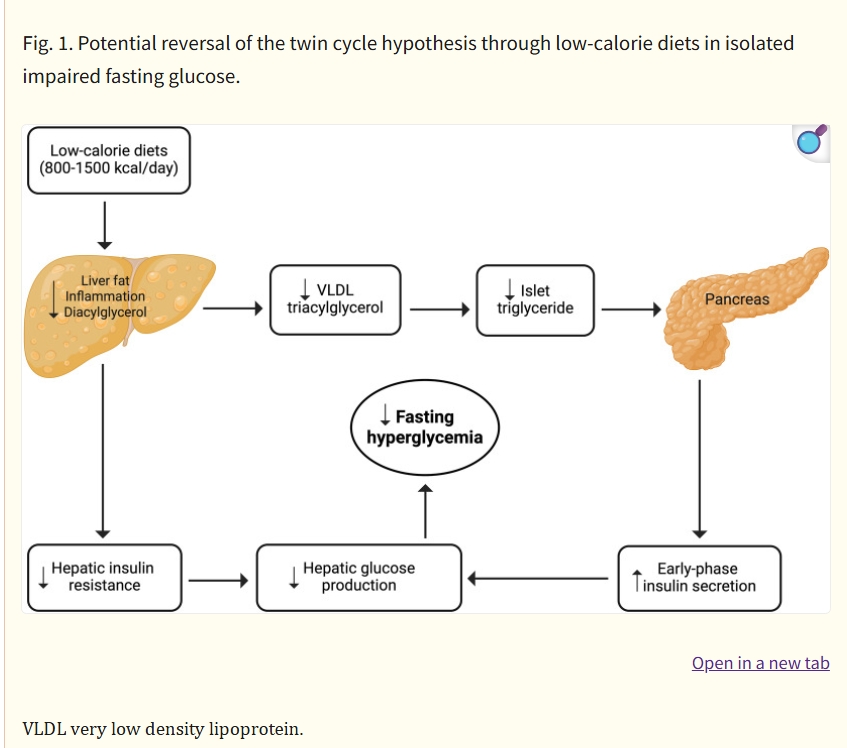
In recent years, low-calorie diets ranging from 800–1500 kcal/day have gained significant attention in managing type 2 diabetes8,16–19. Studies have shown that low-calorie diets can lead to remission and substantial improvements in cardiometabolic risk factors for a significant proportion of individuals with type 2 diabetes8,16–19. These diets are generally well-tolerated and safe, with only mild side effects reported. Table 1 summarizes the key low-calorie diet studies conducted in people with type 2 diabetes8,16–19. Studies implementing low-calorie diets over a 2–5 month period, primarily high in protein and low in fat, have resulted in a mean weight loss of 7–15 kg (8–15% of initial body weight). This level of weight loss was accompanied by a notable reduction in hepatic fat and improved hepatic insulin sensitivity and first-phase insulin secretion. As a result, fasting plasma glucose levels decreased significantly by 27.8 to 43.2 mg/dL. This suggests that low-calorie diets may also be effective for individuals with i-IFG, as they target the pathophysiological defects characterizing this prediabetes phenotype8,16–19. Figure 1 visually depicts the potential reversal of the twin cycle hypothesis through low-calorie diets in individuals with i-IFG. The twin cycle hypothesis20 postulates that chronic excess calorie intake results in increased accumulation of fat in the liver, leading to resistance against insulin’s suppression of hepatic glucose production. Additionally, excess liver fat increases lipid transportation to the pancreas, impairing β-cell function and further promoting hepatic glucose production. These self-reinforcing cycles between the liver and pancreas ultimately result  in the onset of hyperglycemia.

Low-calorie diets for people with isolated impaired fasting glucose – Commun Med (Lond) . 2024 Mar 1;4:35. doi: 10.1038/s43856-024-00466-2

The Plan

  • Eat less
  • Move more
  • Drink less beer

I like to keep things simple.

High Altitude and Diabetes Risk (in mice)

In findings published in Cell Metabolism, the team demonstrated that red blood cells can alter their metabolism when oxygen levels drop. This shift allows the cells to deliver oxygen to tissues more efficiently at high altitude. At the same time, it lowers circulating blood sugar, offering a potential explanation for reduced diabetes risk. Gladstone Institutes. “Scientists discover why high altitude protects against diabetes.” ScienceDaily https://www.sciencedaily.com/releases/2026/02/260221060952.htm (accessed February 21, 2026).

Journal Reference:

  1. Yolanda Martí-Mateos, Zohreh Safari, Shaun Bevers, Ayush D. Midha, Will R. Flanigan, Tej Joshi, Helen Huynh, Brandon R. Desousa, Skyler Y. Blume, Alan H. Baik, Stephen Rogers, Aaron V. Issaian, Allan Doctor, Angelo D’Alessandro, Isha H. Jain. Red blood cells serve as a primary glucose sink to improve glucose tolerance at altitude. Cell Metabolism, 2026; DOI: 10.1016/j.cmet.2026.01.019

How To Reduce Your Risk of Developing Diabetes

The researchers, from 23 universities in Spain and Harvard Chan School, split 4,746 PREDIMED-Plus participants into an intervention group and a control group and followed their health outcomes for six years. The intervention group adhered to a Mediterranean diet; reduced their caloric intake by about 600 calories per day; engaged in moderate physical activity, such as brisk walking and strength and balance exercises; and received professional support for weight loss control. The control group adhered to a Mediterranean diet without calorie restriction, exercise guidance, or professional support. Participants ranged from age 55 to 75, were overweight or obese, and had metabolic syndrome, but were free of T2D at baseline.

The study found that those in the intervention group had a 31% lower risk of developing T2D compared to those in the control group. Additionally, the intervention group lost an average of 3.3 kilograms and reduced their waist circumference by 3.6 centimeters, compared to 0.6 kilograms and 0.3 centimeters in the control group. Scientists found 3 simple tweaks that cut diabetes risk by 31% – https://www.sciencedaily.com/releases/2025/08/250829022835.htm Harvard T.H. Chan School of Public Health. ScienceDaily. http://www.sciencedaily.com/releases/2025/08/250829022835.htm (accessed August 29, 2025).

Guess I’ll cut out beer.

Compounding Compounds the Problem

Compound pharmacies that bulk produce weight-loss drugs without FDA approval are doing so without that oversight.  And because compounding pharmacies aren’t required to report instances of patient harm involving their medications, problems may go undetected.“It’s kind of like ‘Whack-A-Mole,’” said Al Carter, a pharmacist and executive director at the National Association of Boards of Pharmacy. He said state boards will only investigate when they receive a complaint.“There are bad actors out there, purporting to be compounding pharmacies that are licensed in specific states or have the credentials to be able to compound when in actuality they don’t,” said Carter. “My understanding is most licensed, legitimate pharmacies aren’t compounding” weight-loss medications. ‘Compounded’ weight-loss drugs are a growing problem for state regulators – https://stateline.org/2024/07/08/compounded-weight-loss-drugs-are-a-growing-problem-for-state-regulators/

A website sold patients obesity drugs at affordable rates. Now they’re paying the price.– https://www.npr.org/2025/02/08/nx-s1-5246124/a-website-sold-patients-obesity-drugs-at-affordable-rates-now-theyre-paying-the-price

“The two main goals of the medication are weight loss and diabetes management, so patients should stay on the lowest dosage possible until they feel like they’ve plateaued,” said Charu Sawhney, DO, MPH, an internal medicine physician with Harbor Health in Round Rock, Texas. When patients move up on the dosage too fast, they’re going to have more trouble, said Sawhney. “This is when we see the most severe side effects like the malnutrition and dehydration that can sometimes land patients in the hospital,” she said. Considerations for Prescribing GLP-1s Get More Complicated – Medscape – February 07, 2025 – https://www.medscape.com/viewarticle/considerations-prescribing-glp-1s-get-more-complicated

I admit as a Former Fat Man that the world of obesity and now a miracle drug to fight the disease fascinates the hell out of me. Caveat emptor!

The T2D-GENE Trial

The prevalence of type 2 diabetes was significantly lower in the lifestyle intervention group than in the control group.

University of Eastern Finland. “Type 2 diabetes can be prevented by diet and exercise even in individuals with a high genetic risk.” ScienceDaily. http://www.sciencedaily.com/releases/2024/08/240807122749.htm (accessed August 10, 2024).

Effects of Genetic Risk on Incident Type 2 Diabetes and Glycemia: The T2D-GENE Lifestyle Intervention Trial – The Journal of Clinical Endocrinology & Metabolism, dgae422, https://doi.org/10.1210/clinem/dgae422

Remember, Stay as Thin as You Can as Long as You Can.

Statins Raise Diabetes Risk (but CV Benefit Outweighs the Risk)

Statins raise the risks for increased glucose levels and the development of type 2 diabetes among people who don’t have it at baseline, but those risks are outweighed by the cardiovascular benefit, new data suggested.

The meta-analysis of trials in the CTT Collaboration included individual participant data from 19 double-blind randomized, controlled trials with a median follow-up of 4.3 years comparing statins with placebo in a total of 123,940 participants, including 18% who had known type 2 diabetes at randomization. Also analyzed were another four double-blind trials of lower- vs higher-intensity statins involving a total of 30,724 participants followed for a median of 4.9 years, with 15% having diabetes at baseline.

In the 19 trials of low- or moderate-intensity statins vs placebo, statins resulted in a significant 10% increase in new-onset diabetes compared with placebo (rate ratio, 1.10), while high-intensity statins raised the risk by an also significant 36% (1.36). This translated to a mean absolute excess of 0.12% per year of treatment.

Compared with less intensive statin therapy, more intensive statin therapy resulted in a significant 10% proportional increase in new-onset diabetes (1.10), giving an absolute annual excess of 0.22%

In an accompanying editorial, Hertzel C. Gerstein, MD, and Marie Pigeyre, MD, PhD, both of McMaster University and Hamilton Health Sciences, Hamilton, Ontario, Canada, noted that the decreased absolute annual incidence of life-threatening cardiovascular outcomes with statins in people at high risk for type 2 diabetes “clearly exceeds the 0.1%-1.3% per year increased absolute incidence of type 2 diabetes.”

Statins Raise Diabetes Risk, but CV Benefit Outweighs It – Medscape – April 09, 2024. — https://www.medscape.com/viewarticle/statins-raise-diabetes-risk-cv-benefit-outweighs-it