I Stopped Drinking Alcohol Every Day (bonus Scary Chart)

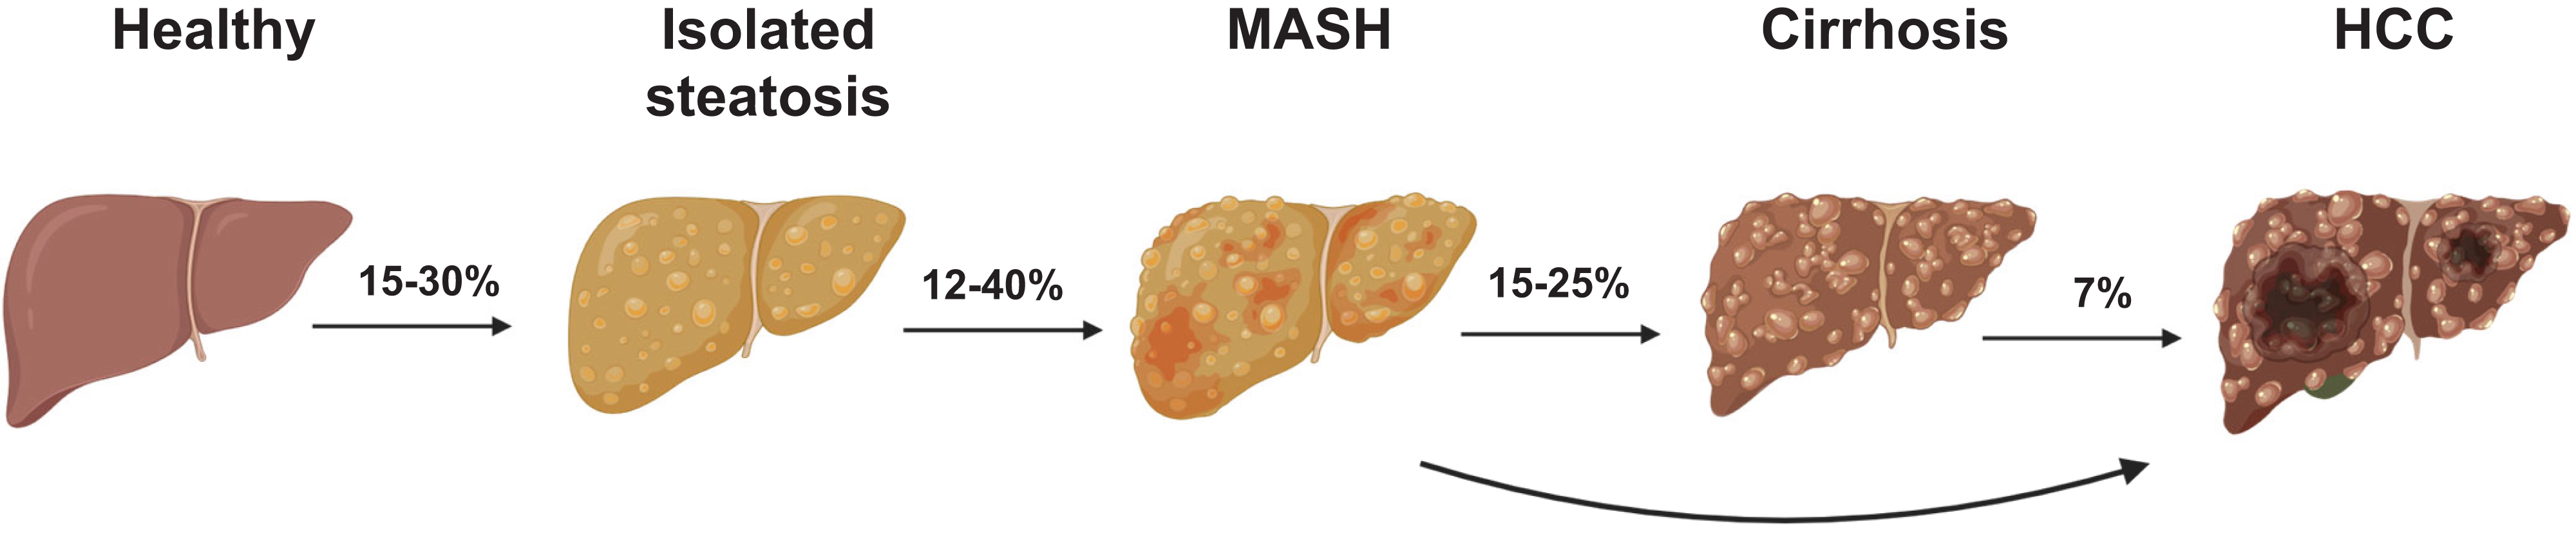
Worldwide, MASLD became the most common chronic liver disease, affecting up to 38% of the adult population (11). In addition, the global prevalence of MASLD is expected to further increase during the next two decades (12). For example, in the U.S., the prevalence of MASLD is predicted to increase from 34% (86 million people) in 2020 to 41% (122 million people) by 2050 (13). MASLD is an increasingly important contributor not only to liver-related but also to extrahepatic morbidity and mortality worldwide. This observation supports that the clinical burden of MASLD clearly extends far beyond the liver, making it a multisystem disorder. While among people with MASLD <10% develop liver-related complications, the major causes of death are CVD and cancer (11,14).

Today, the highest global pooled prevalence of MASLD is found among people with obesity (75% [95% CI 71–79]) (15) and type 2 diabetes (65% [61–68]) (16). Among people with obesity (34% [28–39]) and people with diabetes (32% [17–51]) there is also a very high prevalence of the advanced form of MASLD, metabolic dysfunction–associated steatohepatitis (MASH) (15,16). Furthermore, at 37% (95% CI 26–48), the prevalence of MASLD is also very high among children and adolescents with type 2 diabetes (17). This very early onset of MASLD may have severe long-term consequences for the liver, such as higher risk for cirrhosis and hepatocellular carcinoma (HCC). In addition, among adults with prediabetes prevalence of MASLD is approximately twofold higher in comparison with people with normal glucose regulation, independently of adiposity (18). The findings that overweight and hyperglycemia are tightly related to MASLD indicate that there are joint pathomechanisms promoting adiposity, hyperglycemia, and MASLD. Furthermore, hyperglycemia may promote hepatic steatosis and inflammation, and the steatotic and inflamed liver may also be involved in the pathogenesis of type 2 diabetes. Thus, there may be a vicious cycle between increased liver fat content and insulin resistance–associated hyperglycemia promoting the progression of both diseases.

Norbert Stefan; MASLD as Complication of Diabetes. Diabetes 20 July 2026; 75 (8): 1359–1370. https://doi.org/10.2337/dbi26-0001

The US Health and Human Services (HHS) and Department of Agriculture (USDA) issued new alcohol guidelines in January 2026 “Consume less alcohol for better overall health” and I take advice from my government seriously.

Need. More. Steps.

Walking is the most preferred PA mode for older adults [4] and increasing daily step count may reduce the presence of frailty. Observational research finds a dose-response relationship with higher daily step counts associated with lower frailty prevalence [5]. This relationship persists even among those with very low step counts (less than 3,000 per day) suggesting any increase in step counts may reduce frailty presence. Step counts can be increased by walking for longer durations or walking faster for the same duration. Observed as the 6th vital sign, gait speed is a key frailty indicator, as slow gait speed is one of the most frequently observed and prevalent criteria of frailty [6]. Since gait speed predicts mortality, falls, loss of independence, and cognitive decline [7], and is an important clinical metric of overall health [8], interventions which improve capacity to ambulate faster and over longer distances (e.g., a greater volume of activity) may be particularly therapeutic for those with frailty…

This is the first study to demonstrate that HIW can reverse frailty in older adults with frailty. After 16 weeks, HIW participants had significantly higher odds of improving at least one SHARE-FI frailty category compared to CSW participants. Numerous prior studies have investigated physical activity, multicomponent training, resistance exercise, and nutrition3,9 to improve capacity and physical function, rather than directly modifying the frailty syndrome. In a systematic review of 26 PA intervention studies for frailty, only one study used an aerobic intervention, and this study did not measure frailty as a primary outcome. [25]. In studies that have used frailty as a primary outcome, minimal benefit has been found. Huang et. al, found a 0.02 reduction in frailty index after 26 weeks of training twice-weekly at 70% of heart rate reserve, which did not meet the 0.03 threshold for clinical meaningful change in frailty index scores [26,27]. The combination of aerobic and resistive aerobic activities in our approach may have provided sufficient neuromuscular stimulus by increasing frequency and intensity of activity, despite a shorter intervention duration, to drive improvements in frailty category. Our study advances evidence for the optimal dose of therapeutic interventions for the frailty and provides clear evidence on the substantial benefits of high-intensity walking to decrease and reverse frailty among those with existing frailty. Our approach, which incorporated some resistance elements into aerobic training, was distinct.

Citation: Danilovich M, Rubin DS, Conroy DE, Diaz L, Cheung Y, Corcos D, et al. (2026) A high intensity vs. casual speed walking intervention to reverse frailty among older adults: a cluster randomized controlled trial. https://journals.plos.org/plosone/article?id=10.1371/journal.pone.0357605

But first, must get these Chinknees fixed.

How To Reduce Your DM2 Risk 31%

The results, published in Annals of Internal Medicine, were based on 4,746 adults between ages 55 and 75. All had overweight or obesity and metabolic syndrome, but none had diabetes or cardiovascular disease at the start of the study. Researchers followed participants for six years to see whether a more intensive Mediterranean based lifestyle plan could offer stronger protection against type 2 diabetes than the traditional Mediterranean diet alone.

One group followed a calorie reduced Mediterranean diet (about 600 kcal fewer per day), added moderate physical activity (brisk walking, strength and balance training), and received professional guidance. The comparison group followed a traditional Mediterranean diet without calorie restriction or exercise advice.

The difference between the two approaches was striking. Participants in the intervention group were 31% less likely to develop type 2 diabetes than those in the comparison group. Universidad de Navarra. “Scientists found a smarter Mediterranean diet that slashes diabetes risk by 31%.” ScienceDaily. https://www.sciencedaily.com/releases/2026/05/260519003103.htm (accessed May 23, 2026).

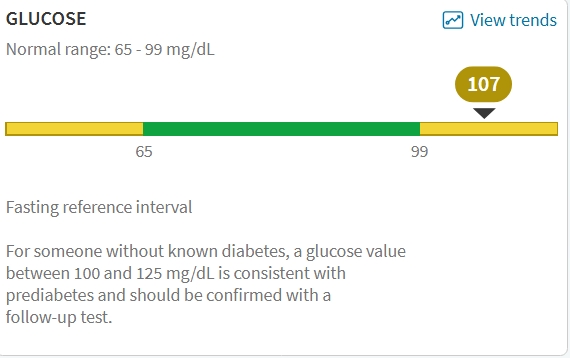
I just had my annual wellness check and got my lab results. All good except my fasting glucose.

Yikes. Memo to Self, get an A1C. Well, the very next day…

Doc says:

CMP (Comprehensive Metabolic Panel): Your creatinine (a measure related to kidney function) is low, and your blood sugar (glucose) is high; all other values are normal. This test checks how your kidneys and liver are working, your body salts, proteins, and blood sugar. Low creatinine can happen in people with less muscle and may be expected. The slightly high fasting blood sugar could indicate early changes in how your body handles sugar. Options include repeating the blood sugar test next visit.

I know my diet could be better. I know I should eat less, snack less and maybe, just maybe stop drinking beer. But also knowing my IFG is worsening I wondered if there was a diet (besides MedDiet) for IFG?

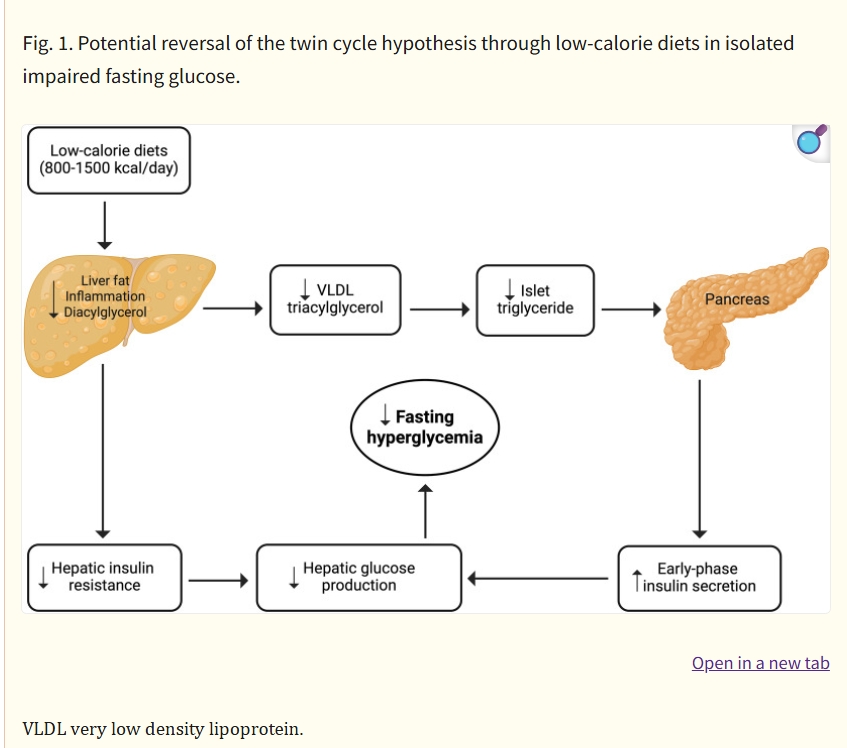
In recent years, low-calorie diets ranging from 800–1500 kcal/day have gained significant attention in managing type 2 diabetes8,16–19. Studies have shown that low-calorie diets can lead to remission and substantial improvements in cardiometabolic risk factors for a significant proportion of individuals with type 2 diabetes8,16–19. These diets are generally well-tolerated and safe, with only mild side effects reported. Table 1 summarizes the key low-calorie diet studies conducted in people with type 2 diabetes8,16–19. Studies implementing low-calorie diets over a 2–5 month period, primarily high in protein and low in fat, have resulted in a mean weight loss of 7–15 kg (8–15% of initial body weight). This level of weight loss was accompanied by a notable reduction in hepatic fat and improved hepatic insulin sensitivity and first-phase insulin secretion. As a result, fasting plasma glucose levels decreased significantly by 27.8 to 43.2 mg/dL. This suggests that low-calorie diets may also be effective for individuals with i-IFG, as they target the pathophysiological defects characterizing this prediabetes phenotype8,16–19. Figure 1 visually depicts the potential reversal of the twin cycle hypothesis through low-calorie diets in individuals with i-IFG. The twin cycle hypothesis20 postulates that chronic excess calorie intake results in increased accumulation of fat in the liver, leading to resistance against insulin’s suppression of hepatic glucose production. Additionally, excess liver fat increases lipid transportation to the pancreas, impairing β-cell function and further promoting hepatic glucose production. These self-reinforcing cycles between the liver and pancreas ultimately result  in the onset of hyperglycemia.

Low-calorie diets for people with isolated impaired fasting glucose – Commun Med (Lond) . 2024 Mar 1;4:35. doi: 10.1038/s43856-024-00466-2

The Plan

  • Eat less
  • Move more
  • Drink less beer

I like to keep things simple.

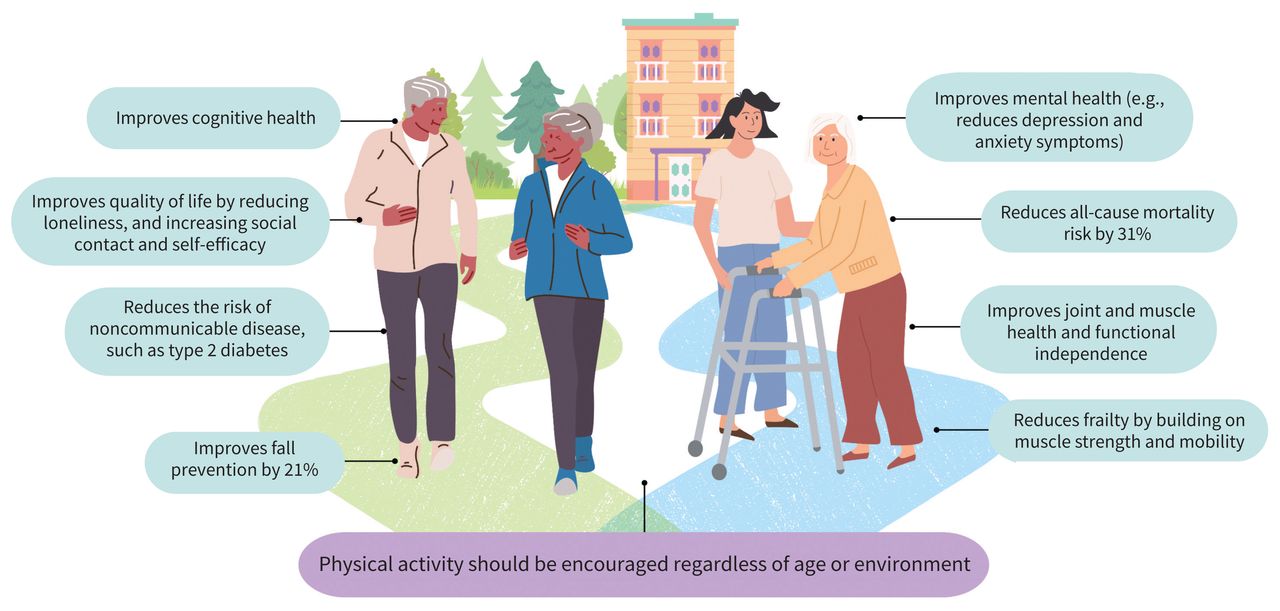
Benefits of Physical Activity in Older Adults

Benefits of physical activity in older adults.

Longevity

The association between physical activity and mortality and morbidity is well established. A 2023 meta-analysis of large prospective studies that examined dose–response found that physical activity levels equivalent to the recommended 150 minutes per week of moderate physical activity reduced all-cause mortality by 31% compared with no physical activity.12 The authors used metabolic equivalent of task (MET), the ratio of work metabolic rate to resting metabolic rate. One MET is equivalent to the energy cost of sitting quietly. A 2019 systematic review and meta-analysis found that, among middle-aged and older adults (aged ≥ 40 yr), higher levels of total physical activity were associated with reduced risk of death in a dose–response relation, such that the most, second-most, and third-most active quartiles were associated with 0.47, 0.35, and 0.28 hazard ratios, respectively, compared with the least active quartile.13 According to a large 2019 observational study, resistance exercise is also associated with reduced mortality independent of aerobic exercise.14 Two 2022 meta-analyses found, respectively, that 60 minutes of resistance exercise per week is associated with a risk reduction of 27% in all-cause mortality15 and that muscle-strengthening activities for 30–60 minutes per week is associated with a 10%–20% reduction.16

Cardiorespiratory fitness and peak exercise capacity are associated with mortality. Peak exercise capacity is a better indicator of risk of death than established cardiovascular risk factors such as smoking, hypertension, and diabetes mellitus.17 A study examining cardiorespiratory fitness in older adults found dose-dependent reductions in mortality across all age groups (including participants aged 60–69, 70–79, and 80–95 yr).18 Substantial improvements (approximately 16%) in VO2max (an individual’s maximum rate of oxygen consumption, a strong indicator of mortality19) in older adults can occur with only 90 minutes of submaximal exercise per week over 16–20 weeks.20

Strength is also associated with reductions in all-cause mortality in older adults. A 2022 systematic review and meta-analysis found a linear inverse relation between handgrip strength and all-cause mortality up to sex-dependent thresholds (42 kg for men, 25 kg for women) in older adults.21 In their 2018 systematic review and meta-analysis, the authors found both handgrip and knee extension strength to be predictors of all-cause mortality in adults, with most of the studies examining adults older than 65 years.22 – Move more, age well: prescribing physical activity for older adults CMAJ January 27, 2025 197 (3) E59-E67; DOI: https://doi.org/10.1503/cmaj.231336

Chronic Pain? Check This Out

Curiosity is not a curse. I’ve been expanding my knowledge base this morning.

As I have written before, the key to treating chronic pain often lies in therapies designed to dampen the brain’s response to pain signals. In treating my own chronic pain, I benefited greatly from a mindfulness therapist who helped me develop techniques to redirect thoughts and feelings of pain, push them out of my body. In my case, I met virtually with the therapist, who expertly sussed out my situation and tailored her advice to my needs. She worked at Duke University, in one of their pain clinics, and was an expert at helping people like me. This Online Program Could Be The Solution To Your Chronic Pain – https://www.forbes.com/sites/peterubel/2026/02/07/this-online-program-could-be-the-solution-to-your-chronic-pain/

Here’s the link to Telehealth and Online Cognitive Behavioral Therapy–Based Treatments for High-Impact Chronic Pain A Randomized Clinical Trial – https://jamanetwork.com/journals/jama/fullarticle/2836795 Conclusions and Relevance  Remote, scalable CBT-CP treatments (delivered either via telehealth or self-completed modules online) resulted in modest improvements in pain and related functional/quality-of-life outcomes compared with usual care among individuals with high-impact chronic pain. These lower-resource CBT-CP treatments could improve availability of evidence-based nonpharmacologic pain treatments within health care systems.

Here’s the link to the online resource quoted in the Forbes article https://mypaintrainer.org/login-to-paintrainer/

Full disclosure:

I’ve had chronic pain since 1976 (or was it 1977?) when I had a near fatal encounter with a fast moving car while walking home. I don’t take any pain medications other than the occasional ibuprofen. I have been using an online pain management resource courtesy of my employer (not the resource linked above). A DPT (Doctor of Physical Therapy) and health coach are part of the resources at my disposal. I haven’t used any ibuprofen in quite some time, if that tells you anything.

I will be exploring https://mypaintrainer.org/login-to-paintrainer/ more but at the time of this writing have not looked into their services.

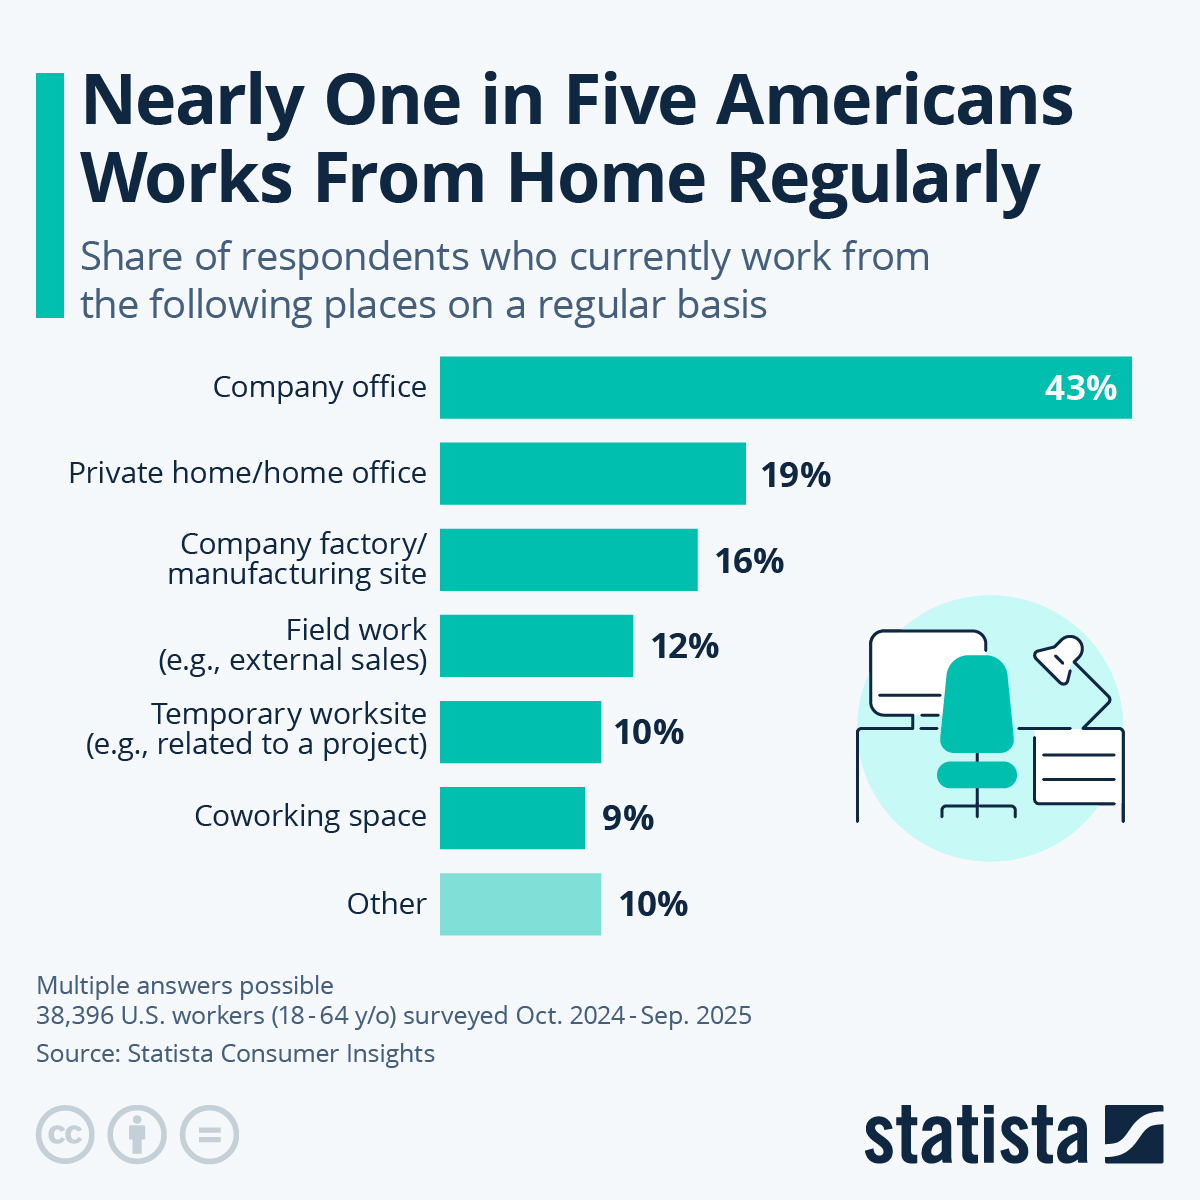
Remote Work – Not The Norm

Nearly One in Five Americans Works From Home Regularly – https://www.statista.com/chart/35389/regular-remote-and-home-office-work/

I started writing my journal in 2005. One of the best things about keeping a journal is the ability to verify if memories from the past are accurate or the made up, mashups your brain creates as memories. Here’s my entry on Monday July 24 2006:

A 4:00 PM meeting with the Division head with an HR rep present is never a good thing. I immediately thought to myself:

“This is gonna suck.”

And it did, big time. I got whacked today.

And that’s how my WFH life began. When my work from home situation arises in conversation most are surprised to learn I’ve been WFH this long. I’m surprised how long I’ve been working from home!

I am convinced due to having a low stress working environment, better diet (NO office snacks/free food/lunches out), no commute, along with a host of other variables I just might be increasing my lifespan. I do know I get plenty of sleep on a regular routine basis.

Short sleep duration (< 7 h per night) was associated with a 14% increase in mortality risk compared to the reference of 7–8 h, with a pooled hazard ratio of 1.14 (95% CI 1.10 to 1.18). Conversely, long sleep duration (≥ 9 h per night) was associated with a 34% higher risk of mortality, with a hazard ratio of 1.34 (95% CI 1.26 to 1.42). Sex-specific analyses indicated that both short and long sleep durations significantly elevated mortality risk in men and women, although the effect was more pronounced for long sleep duration in women. Both short and long sleep durations are associated with increased all-cause mortality, though the degree of risk varies by sex. Imbalanced sleep increases mortality risk by 14–34%: a meta-analysis – Ungvari, Z., Fekete, M., Varga, P. et al. Imbalanced sleep increases mortality risk by 14–34%: a meta-analysis. GeroScience 47, 4545–4566 (2025). https://doi.org/10.1007/s11357-025-01592-y

Compounding Compounds the Problem

Compound pharmacies that bulk produce weight-loss drugs without FDA approval are doing so without that oversight.  And because compounding pharmacies aren’t required to report instances of patient harm involving their medications, problems may go undetected.“It’s kind of like ‘Whack-A-Mole,’” said Al Carter, a pharmacist and executive director at the National Association of Boards of Pharmacy. He said state boards will only investigate when they receive a complaint.“There are bad actors out there, purporting to be compounding pharmacies that are licensed in specific states or have the credentials to be able to compound when in actuality they don’t,” said Carter. “My understanding is most licensed, legitimate pharmacies aren’t compounding” weight-loss medications. ‘Compounded’ weight-loss drugs are a growing problem for state regulators – https://stateline.org/2024/07/08/compounded-weight-loss-drugs-are-a-growing-problem-for-state-regulators/

A website sold patients obesity drugs at affordable rates. Now they’re paying the price.– https://www.npr.org/2025/02/08/nx-s1-5246124/a-website-sold-patients-obesity-drugs-at-affordable-rates-now-theyre-paying-the-price

“The two main goals of the medication are weight loss and diabetes management, so patients should stay on the lowest dosage possible until they feel like they’ve plateaued,” said Charu Sawhney, DO, MPH, an internal medicine physician with Harbor Health in Round Rock, Texas. When patients move up on the dosage too fast, they’re going to have more trouble, said Sawhney. “This is when we see the most severe side effects like the malnutrition and dehydration that can sometimes land patients in the hospital,” she said. Considerations for Prescribing GLP-1s Get More Complicated – Medscape – February 07, 2025 – https://www.medscape.com/viewarticle/considerations-prescribing-glp-1s-get-more-complicated

I admit as a Former Fat Man that the world of obesity and now a miracle drug to fight the disease fascinates the hell out of me. Caveat emptor!

It’s 8:00 AM…yes, I’m Thinking About Drinking

Alcohol use is ubiquitous in the United States, with 84% of adults reporting use at some point. Alcohol use disorder (AUD) is a serious and persistent disease at the extreme end of alcohol use that contributes heavily to the burden on the healthcare system, with more than 200,000 hospitalizations each year due to the condition. About 6% of people in the United States have AUD. However, only 7.6% of patients with AUD seek treatment, although several pharmacologic and nonpharmacologic treatment options are available. Stephen Soreff. Rapid Rx Quiz: Alcohol Use Disorder Treatments – Medscape – Dec 30, 2024. https://reference.medscape.com/viewarticle/1002119

  • Overall mortality rates increased from 10.7 (95% CI, 10.6-10.8) per 100,000 in 1999 to 21.6 (95% CI, 21.4-21.8) per 100,000 in 2020, representing a significant twofold increase.
  • Adults aged 55-64 years demonstrated both the steepest increase and highest absolute rates in both 1999 and 2020.
  • American Indian and Alaska Native individuals experienced the steepest increase and highest absolute rates among all racial groups.
  • The West region maintained the highest absolute rates in both 1999 and 2020, despite the Midwest showing the largest increase. Edited by Lora McGlade. US Alcohol-Related Deaths Double Over Two Decades, With Notable Age and Gender Disparities – Medscape – November 21, 2024. https://www.medscape.com/viewarticle/us-alcohol-related-deaths-double-over-two-decades-notable-2024a1000l98?

Nearly 500 years ago, Swiss physician and chemist Paracelsus expressed the basic principle of toxicology: “All things are poison and nothing is without poison; only the dose makes a thing not a poison.” This is often condensed to: “The dose makes the poison.” It means that a substance that contains toxic properties can cause harm only if it occurs in a high enough concentration. https://www.chemicalsafetyfacts.org/health-and-safety/the-dose-makes-the-poison/

Dry January? If you’re doing this trendy behavior you know you drank too much this past holiday season.

Cancer warnings on alcohol? No one will read them.

Trust your intuition. If you’ve ever felt like you drink too much alcohol then you do.

1-800-662-HELP or text 988 for SAMHSA’s National Helpline.

Prostate Cancer Diagnosis? Eat Less Omega-6 fats and More Omega-3 fats

To determine whether diet or supplements can play a role in managing prostate cancer, the UCLA-led team conducted a prospective clinical trial, called CAPFISH-3, that included 100 men with low risk or favorable intermediate risk prostate cancer who chose active surveillance. Participants were randomly assigned to either continue their normal diet or follow a low omega-6, high omega-3 diet, supplemented with fish oil, for one year.

The findings, published in the Journal of Clinical Oncology, show that a diet low in omega-6 and high in omega-3 fatty acids, combined with fish oil supplements, significantly reduced the growth rate of prostate cancer cells in men with early-stage disease.

University of California – Los Angeles Health Sciences. “A low omega-6, omega-3 rich diet and fish oil may slow prostate cancer growth.” ScienceDaily. http://www.sciencedaily.com/releases/2024/12/241213211326.htm (accessed December 13, 2024)

Another reminder I should get my PSA level checked.

My Fat Cells Have a Memory

Even after drastic weight loss, the body’s fat cells carry the ‘memory’ of obesity, research1 shows — a finding that might help to explain why it can be hard to stay trim after a weight-loss programme.

This memory arises because the experience of obesity leads to changes in the epigenome — a set of chemical tags that can be added to or removed from cells’ DNA and proteins that help to dial gene activity up or down. For fat cells, the shift in gene activity seems to render them incapable of their normal function. This impairment, as well as the changes in gene activity, can linger long after weight has dropped to healthy levels, a study published today in Nature reports.

Fat cells have a ‘memory’ of obesity — hinting at why it’s hard to keep weight off – www.nature.com/articles/d41586-024-03614-9

For the geeks, here’s a link to the original study – https://doi.org/10.1038/s41586-024-08165-7

Even without this study I already knew my fat cells have a memory because they are constantly trying to make me gain weight.